PRESCRIPTION (RX)
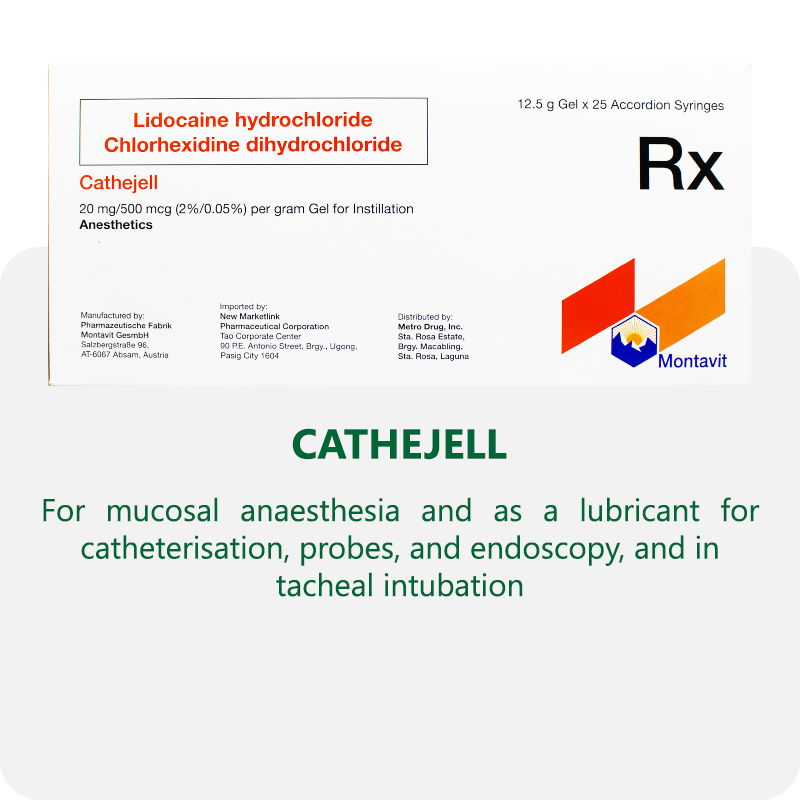
GENERIC NAME: Lidocaine hydrocloride Chlorhexidine dihydrochloride
INDICATION:
For mucosal anasthesia and as a lubricant for catheterisation, probes and endoscopy; and in tracheal intubation.
DOSAGE AND ADMINISTRATION:
Take one (1) capsule orally a day
AVAILABILITY:
12.5 g Gel accordion syringe (Box of 25’s)
NO APPROVED THERAPEUTIC CLAIMS
PRESCRIPTION (RX)
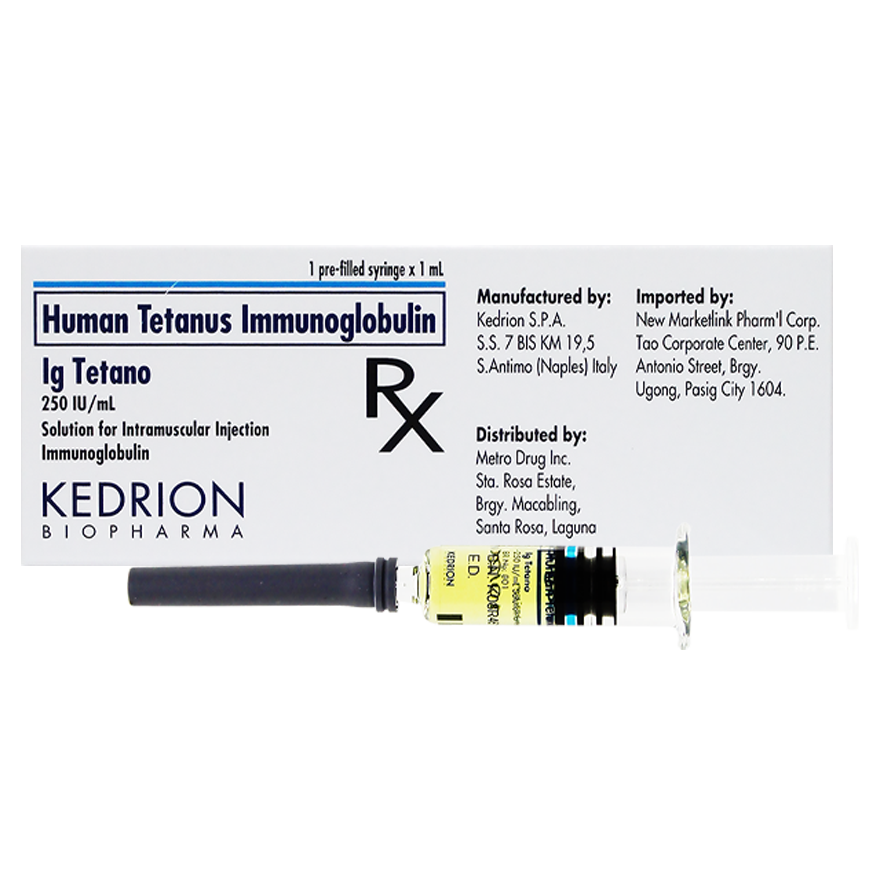
GENERIC NAME: Human Tetanus Immunoglobulin
INDICATION:
Immedetiate prophylaxis after tetanus prone injuries; in patients who are not adequately vaccinated in patients whose immunisation statues is not known with certainty, and in patients with severe deficiency in antibody production.
DOSAGE AND ADMINISTRATION:
250 IU, unless the risk is thought to be extremely high, the dose may be increased to 500 IU.
AVAILABILITY:
1 mL pre-filled syringe
NO APPROVED THERAPEUTIC CLAIMS
PRESCRIPTION (RX)
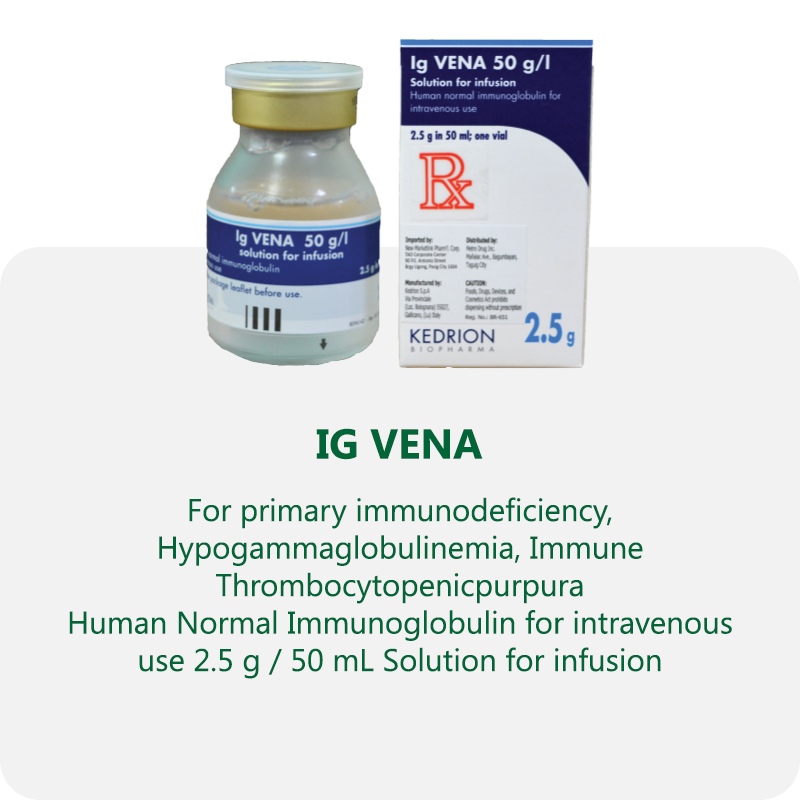
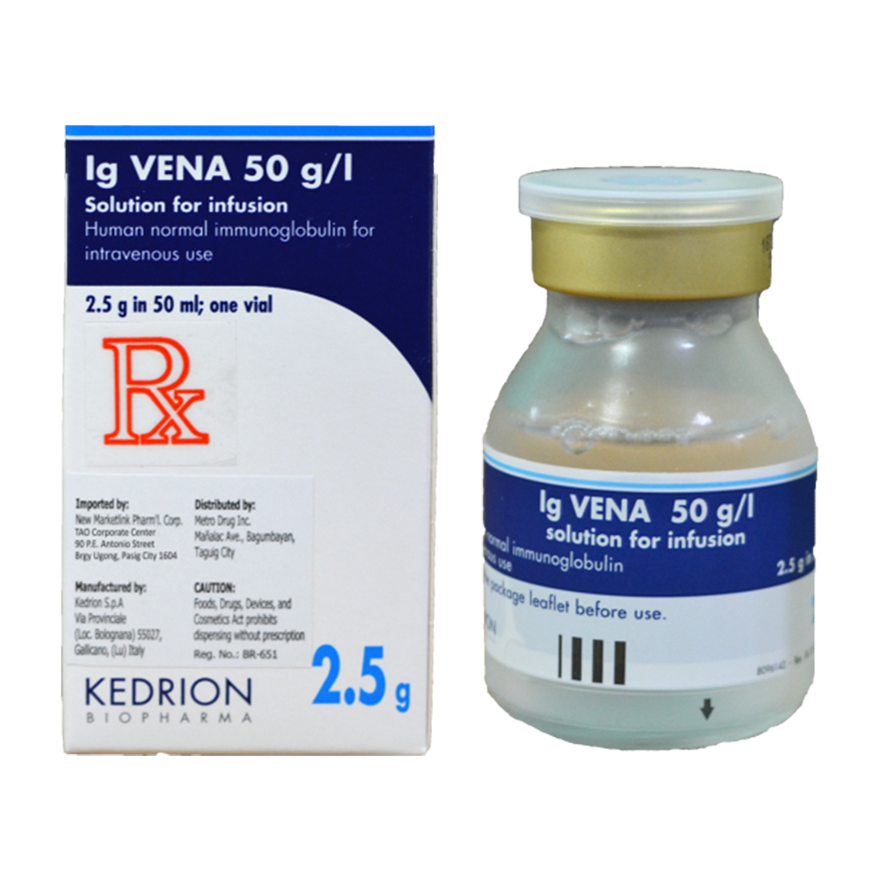
GENERIC NAME: Human Normal Immunoglobulin
INDICATION:
Replacement therapy in primary immunodeficiency syndromes, myeloma or chronic lymphatic leukaemia with severe secondary hypogammaglobulinaemia and recurrent infections. Children with congenital AIDS and recurrent infection, and Immunomodulation. For more detailed information about the product, refer to the FDA-approved package insert.
DOSAGE AND ADMINISTRATION:
The recommended infusion rate is 0.46 – 0.92 mL/kg/hr (10-20 drops per minute) for 20-30 minutes. If well tolerated, the rate of administration may gradually be increased to a maximum of 1.85 mL/kg/hr (40 drops/minute) for the remainder of the infusion.

AVAILABILITY:
Vial human normal immoglobulin 50 mg/mL
NO APPROVED THERAPEUTIC CLAIMS
PRESCRIPTION (RX)
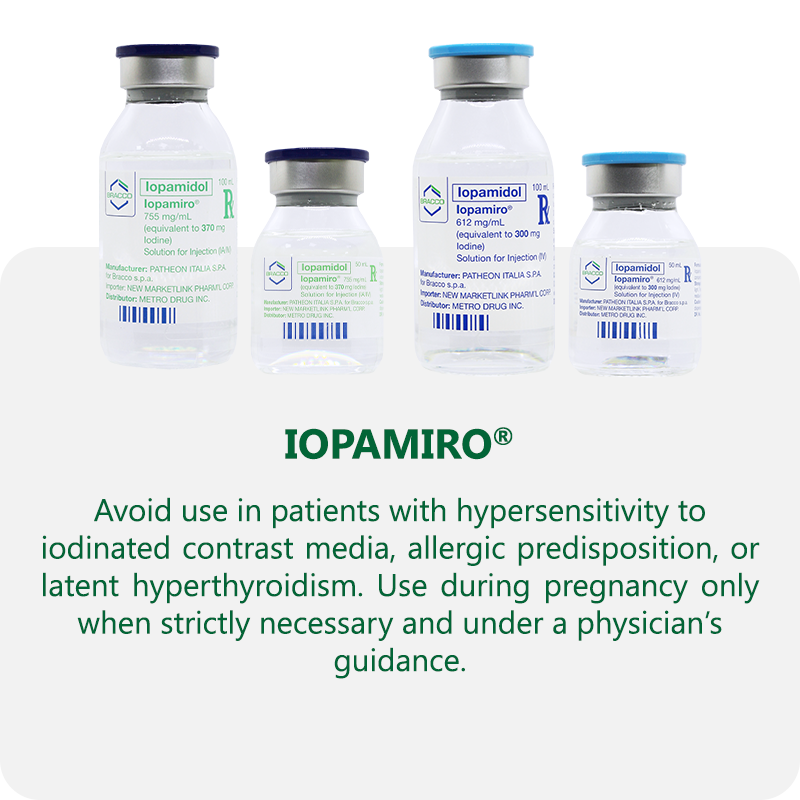
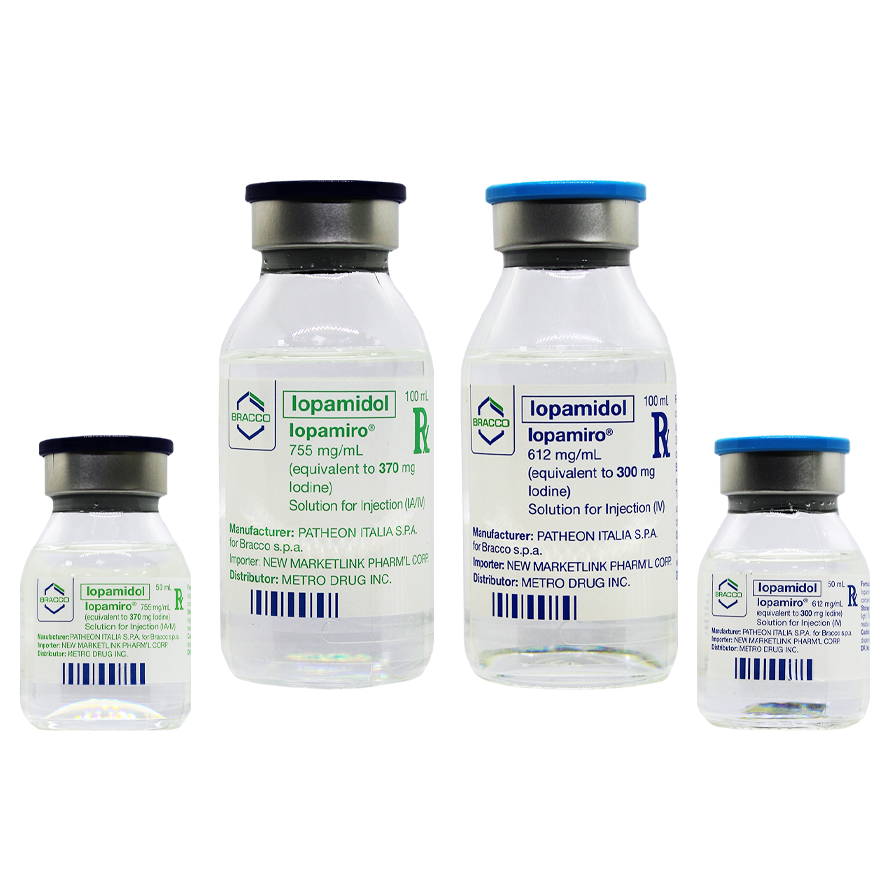
GENERIC NAME: Iopamidol
INDICATION:
Neuroradiology, angiography, urography, contrast enhancement in CT scanning, arthrography, fistulography.
DOSAGE AND ADMINISTRATION:
Hypersensitivity to iodinized contrast media, a general allergic predisposition, or latent hyperthyroidism. Use during pregnancy only when strictly necessary.
AVAILABILITY:
300 mg x 50 and 100 mL vial (Box of 1’s)
370 mg x 50 and 100 mL vial (Box of 1’s)
NO APPROVED THERAPEUTIC CLAIMS
PRESCRIPTION (RX)
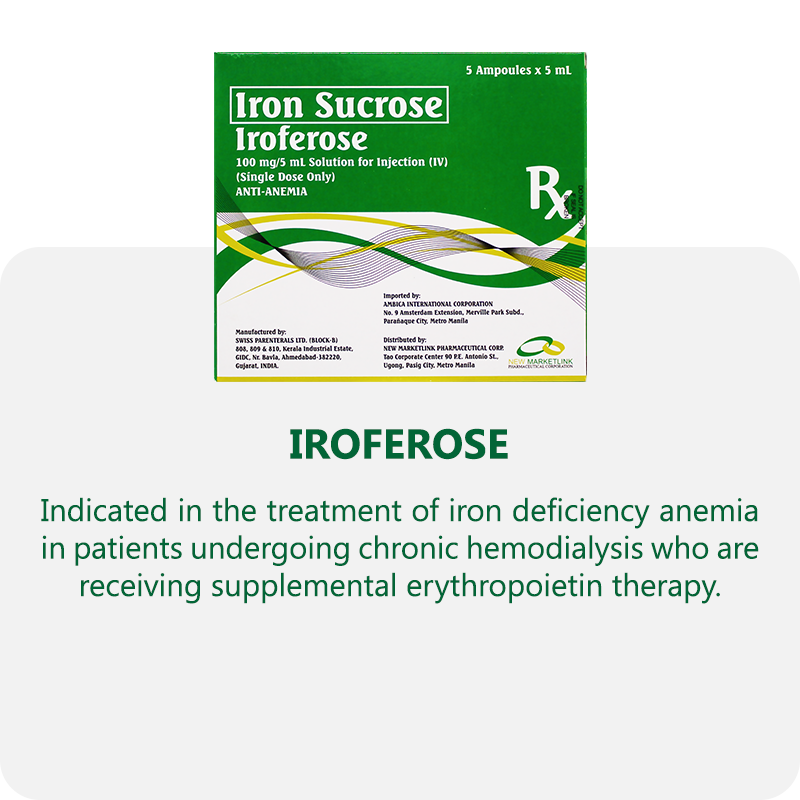
GENERIC NAME: Iron Sucrose
INDICATION:
Indicated in the treatment of iron deficiency anemia in patients undergoing chronic hemodialysis who are receiving supplemental erythropoietin therapy.
DOSAGE AND ADMINISTRATION:
Indicated in the treatment of iron deficiency anemia in patients undergoing chronic hemodialysis who are receiving supplemental erythropoietin therapy.
AVAILABILITY:
USP Type I amber glass ampule x 5 mL (Box of 1 PVC tray x 5’s)
NO APPROVED THERAPEUTIC CLAIMS
PRESCRIPTION (RX)
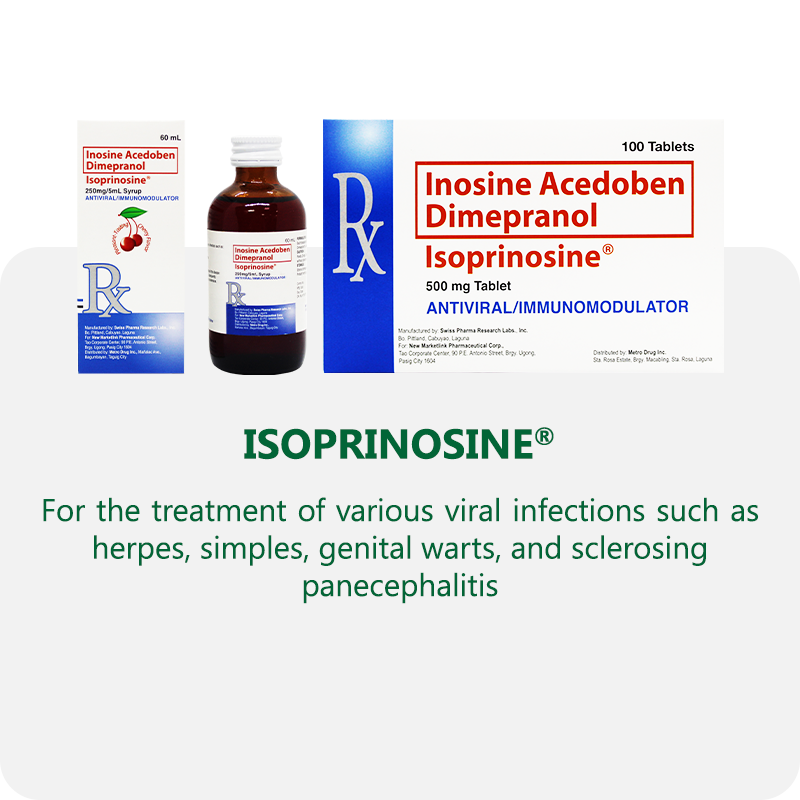
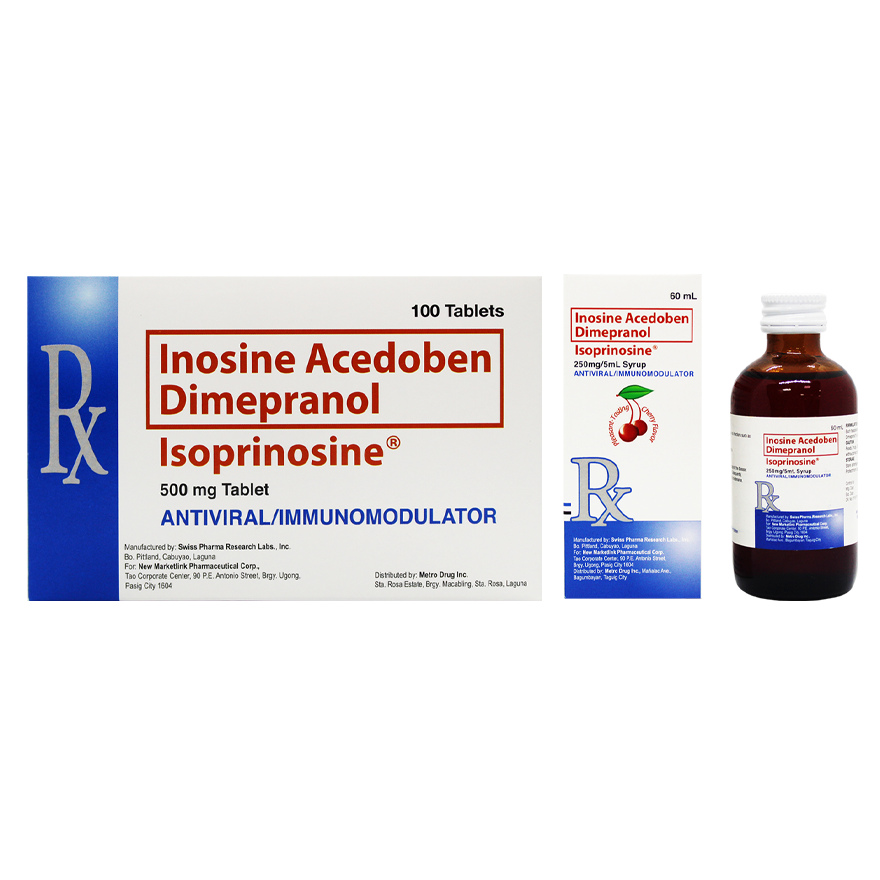
GENERIC NAME: Inosine Acedoben Dimepranol
INDICATION:
For the treatment of various viral infections such as herpes simplex, genital warts, and sclerosing panencephalitis
DOSAGE AND ADMINISTRATION:
Indicated in the treatment of iron deficiency anemia in patients undergoing chronic hemodialysis who are receiving supplemental erythropoietin therapy.
AVAILABILITY:
Isoprinosine 500 mg Tablet (Box of 100’s)
Isoprinosine Syrup 60 mL
NO APPROVED THERAPEUTIC CLAIMS
PRESCRIPTION (RX)
GENERIC NAME: Human Albumin
INDICATION:
Albumin replacement in patients with major albumin deficiency.
DOSAGE AND ADMINISTRATION:
KEDRILAB is ready for use and is to be administered by intravenous infusion only. The infusion rate should be adjusted accroding to individual circumstances and indications; normally be set at 1-2 mL/min. Maximum time for administration is 3 hours. Infusion rate should not exceed 30 mL/min during plasmapheresis. For more detailed information about the product, refer to the FDA-approved package insert.
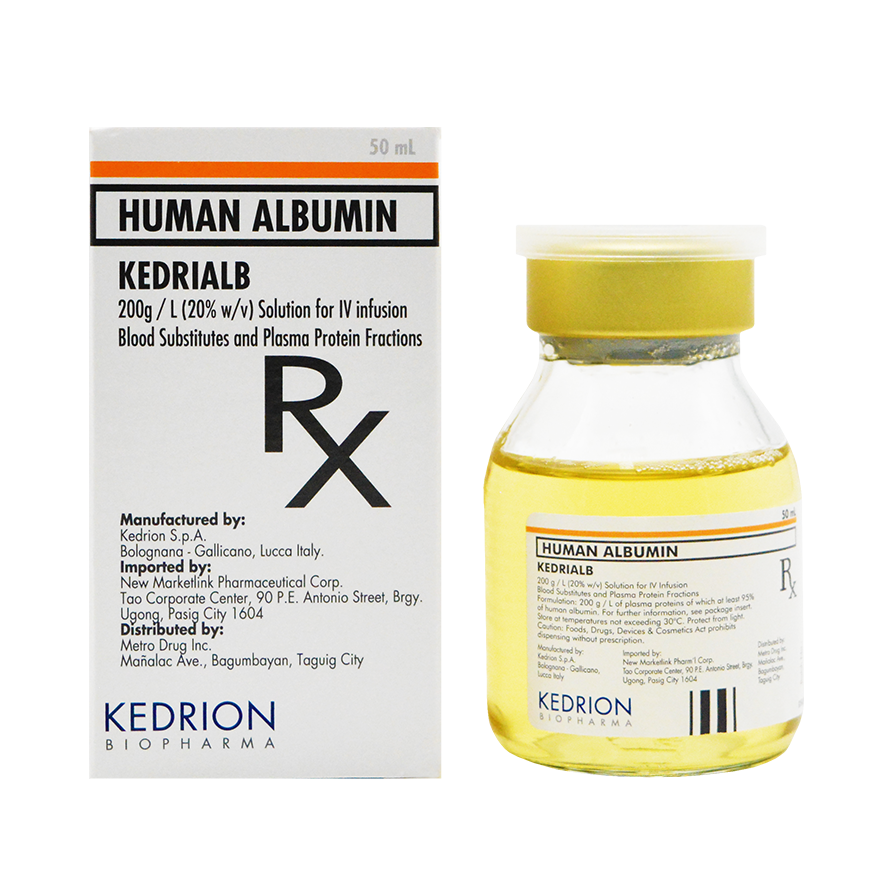

AVAILABILITY:
Solution for IV Infusion x 50 mL
NO APPROVED THERAPEUTIC CLAIMS
PRESCRIPTION (RX)
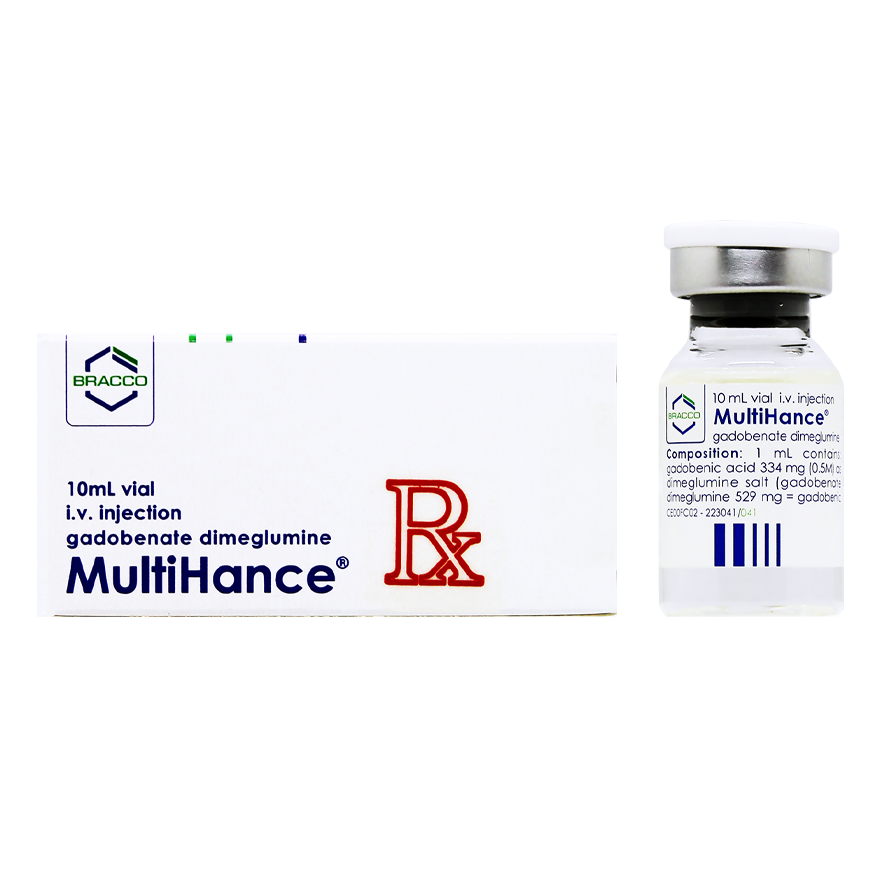
GENERIC NAME: Gadobenate Dimeglumine
INDICATION:
MultiHance is an MRI contrast agent used to improve the detection and diagnosis of lesions and vascular diseases in the liver, brain, spine, breasts, and blood vessels during MRI and MR angiography procedures.
DOSAGE AND ADMINISTRATION:
MultiHance is an MRI contrast agent used to improve the detection and diagnosis of lesions and vascular diseases in the liver, brain, spine, breasts, and blood vessels during MRI and MR angiography procedures.
AVAILABILITY:
10 mL Vial (Box of 1’s)
NO APPROVED THERAPEUTIC CLAIMS
PRESCRIPTION (RX)
GENERIC NAME: Pinene / Camphene / Cineol / Menthol / Borneol / Olive Oil
INDICATION:
For hepatobiliary disorders including cholelithiasis.
DOSAGE AND ADMINISTRATION:
Adults: Unless otherwise directed by the physician, the usual dose id 1-2 capsules three times daily before meals.
Children (6-14 yrs. old): Unless otherwise directed by the physician, the usual dose is one capsule twice daily before meal s.
AVAILABILITY:
100 capsules
NO APPROVED THERAPEUTIC CLAIMS
PRESCRIPTION (RX)
GENERIC NAME: Zinc Oxide + Calcium Carbonate + Bismuth Subgallate + Menthol
INDICATION:
For the treatment of hemorrhoids and proctitis (anal irritation)
DOSAGE AND ADMINISTRATION:
Apply 2-3 times daily and after defecation. For internal hemorrhoids, use the cannula nozzle provided.
AVAILABILITY:
Rowatanal® 10 g ( Box of 1’s)
Rowatanal® 26 g (Box of 1’s)
NO APPROVED THERAPEUTIC CLAIMS
PRESCRIPTION (RX)
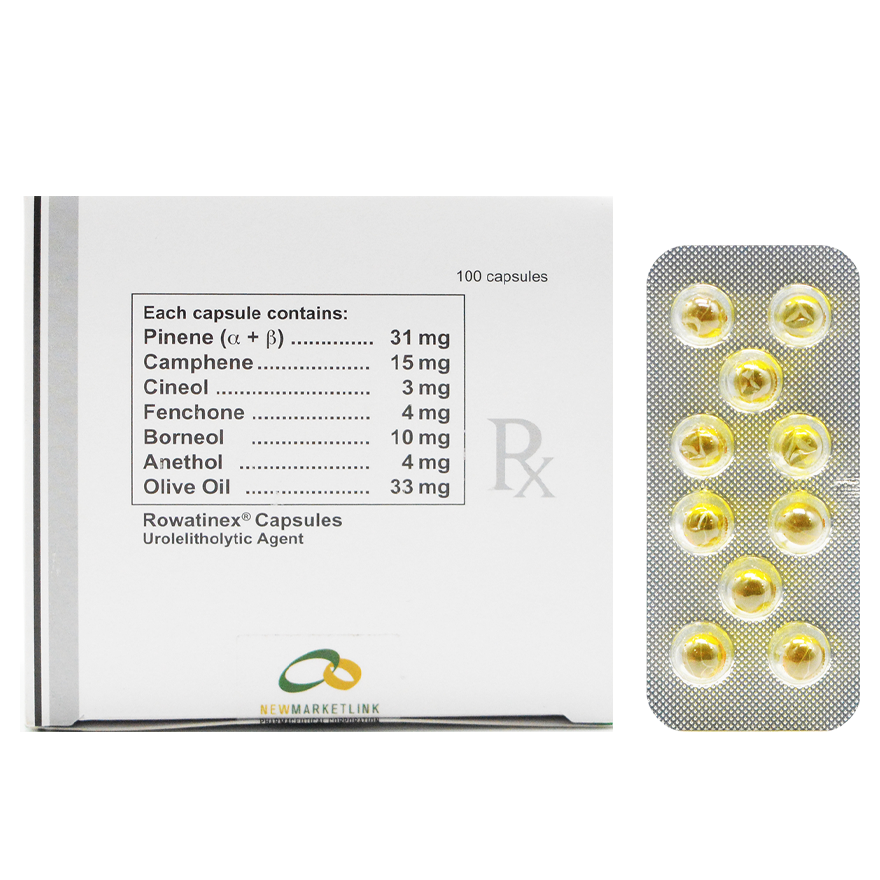
GENERIC NAME: Pinene / Camphene / Cineol / Fenchone / Borneol / Anethol / Olive Oil
INDICATION:
For renal and urinary disorders including urolithiasis.
DOSAGE AND ADMINISTRATION:
Adults: Unless otherwise directed by the physician, the usual dose id 1-2 capsules three times daily before meals.
Children (6-14 yrs. old): Unless otherwise directed by the physician, the usual dose is one capsule twice daily before meals.
AVAILABILITY:
100 capsules
NO APPROVED THERAPEUTIC CLAIMS
PRESCRIPTION (RX)
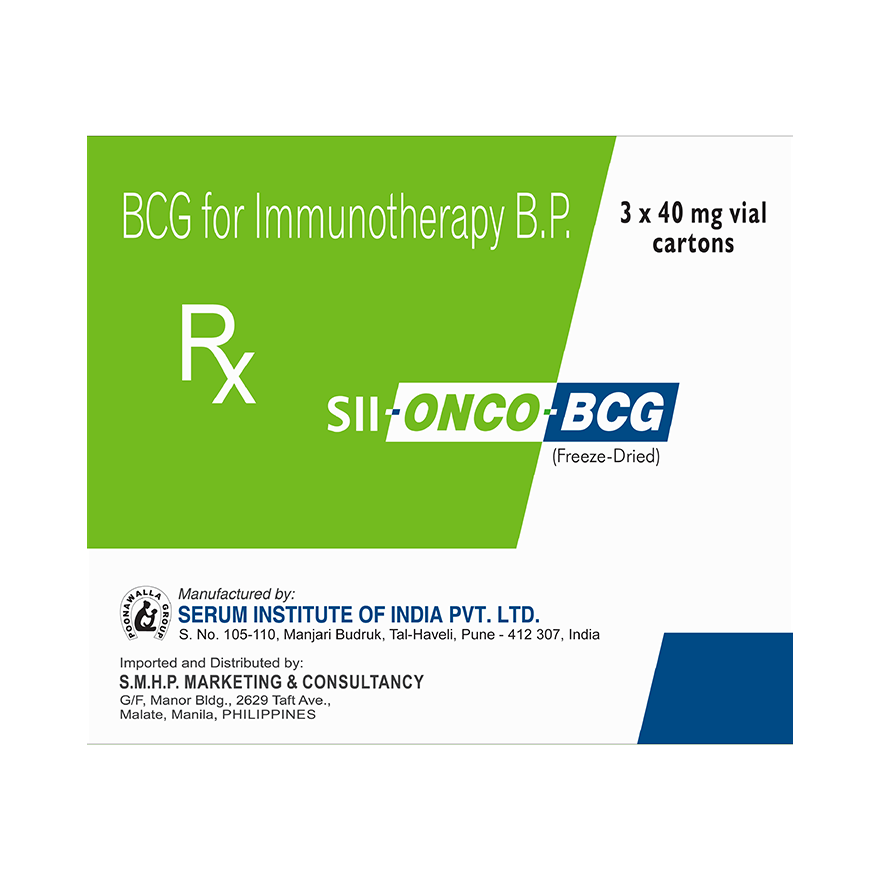
GENERIC NAME: Bacillus Calmette-Guerin (BCG)
INDICATION:
For patients with Superficial Bladder Cancer/Non-Muscle Invasive Bladder Cancer (Stage Ta/T1-Grade 1,2 or 3)
DOSAGE AND ADMINISTRATION:
BCG is given once a week for 6 weeks (Induction Treatment). One Instillation per week for 3 weeks at 3 months (Maintenance Treatment). One Instillation per week for 3 weeks at 6 months. One Instillation per week for 3 weeks after every 6 months until 36 months.
AVAILABILITY:
1 box containing 3 amber glass vials contains each of 40 mg of Bacillus Calmette-Guerin
NO APPROVED THERAPEUTIC CLAIMS
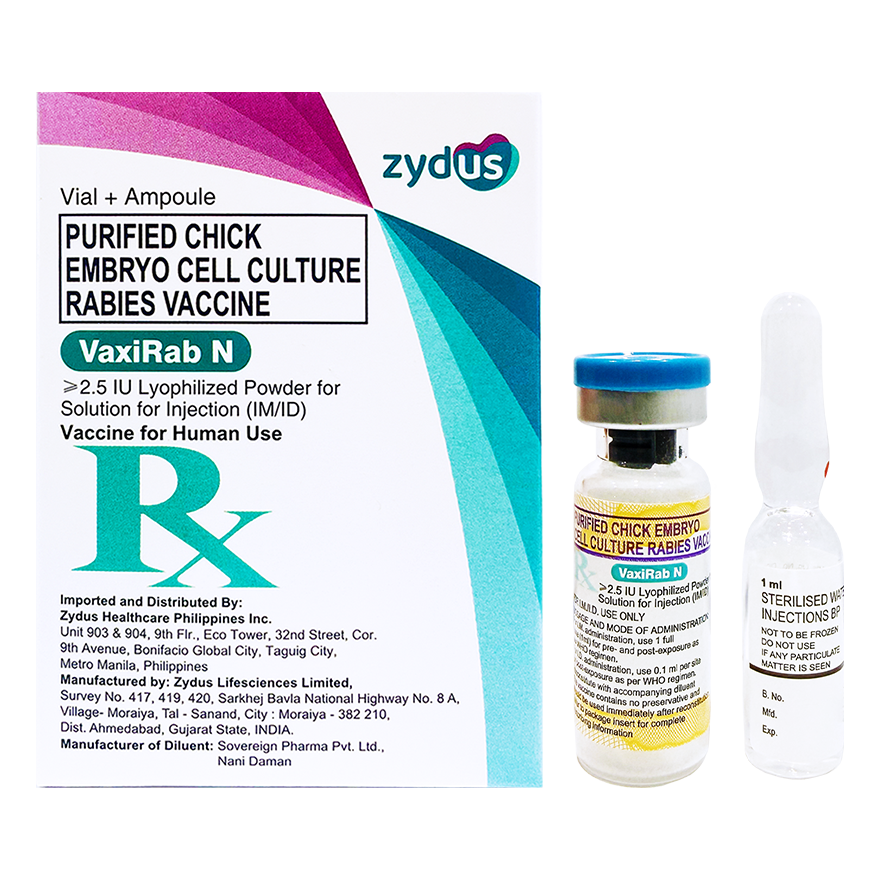
PRESCRIPTION (RX)
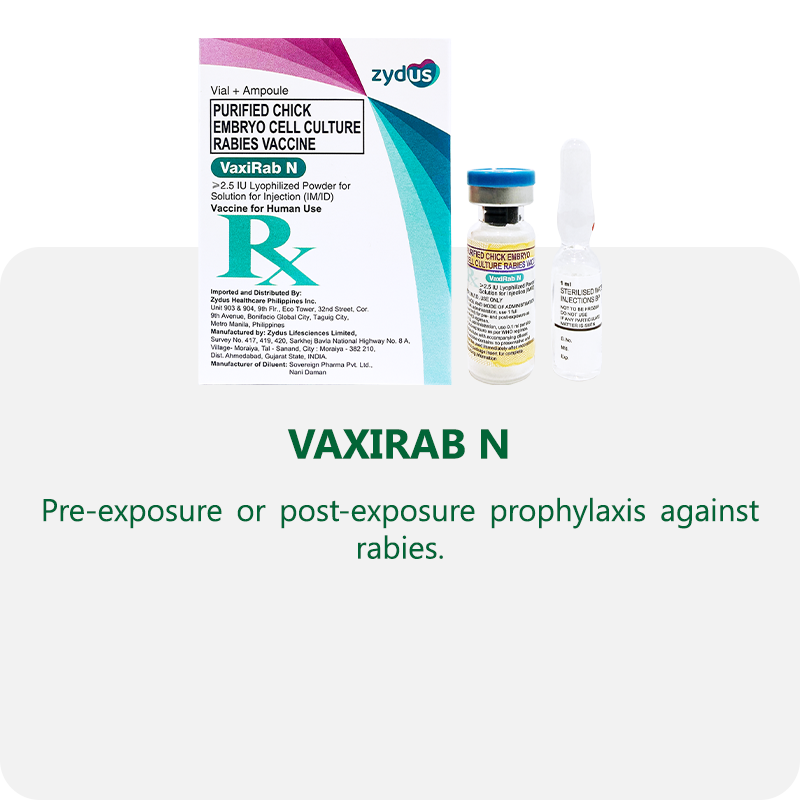
GENERIC NAME: Purified Chick Embryo Culture Rabies Vaccine
INDICATION:
Pre-exposure or post-exposure prophylaxis against rabies.
DOSAGE AND ADMINISTRATION:
Lyophilizied Powder for Solution for Injection (IM/ID)
AVAILABILITY:
1 vial + ampule per box
NO APPROVED THERAPEUTIC CLAIMS
PRESCRIPTION (RX)
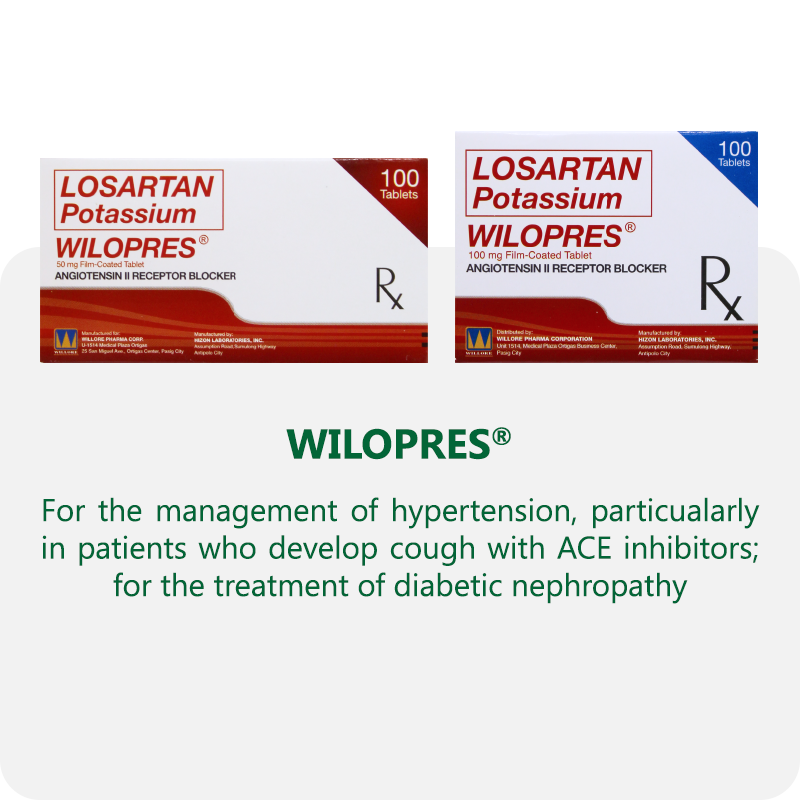
GENERIC NAME: Losartan Potassium
INDICATION:
For the management of hypertension, particularly in patients who develop cough with ACE inhibitors; for the treatment of diabetic nephropathy.
DOSAGE AND ADMINISTRATION:
Usual dose is 50 mg once daily. The dose may be increased to 100 mg, or as prescribed by the physician.
AVAILABILITY:
50 mg Film-coated Tablet: Alu/White PVDC Blister Pack x 10’s (Box of 30’s and 100’s)
100 mg Film-coated Tablet: Alu/White PVDC Blister Pack x 10’s ( Box of 30’s and 100’s)
NO APPROVED THERAPEUTIC CLAIMS
OUR OFFICE
Tao Corporate Center 90 P.E. Antonio St.
Brgy. Ugong Pasig City 1604
CONTACT US AT
(632) (8)836 5838 to 47
EMAIL US AT
mail@nmpc.com.ph
COPYRIGHT © 2026 NEW MARKETLINK PHARMACEUTICAL CORPORATION. ALL RIGHTS RESERVED.

In order to provide you with a better browsing expercience, this website will use cookies. By clicking "Accept" or continuing to browse this website, you agree to our use of cookies.